


A pelvic-floor problem, not something to be embarrassed about
Vaginal Prolapse: Symptoms, Pregnancy and Treatment

Quick answer: vaginal or pelvic organ prolapse means the womb, bladder, bowel or top of the vagina has bulged down into the vagina. It may cause heaviness, dragging, a visible or felt bulge, bladder or bowel trouble, or discomfort during sex—although mild prolapse can have no symptoms. Pregnancy and childbirth are risk factors. If you feel a lump or have symptoms, book a GP or maternity assessment; treatment is based on how much it affects you, not the stage number alone.
A feeling that something is “falling down” can be alarming, especially during pregnancy or after birth. It can also be hard to say out loud. Clinicians have heard the words bulge, pressure, heaviness and “sitting on a ball” many times before; you do not need perfect anatomical vocabulary to ask for help.
Most importantly, prolapse does not automatically mean surgery. Pelvic-health physiotherapy, lifestyle changes and a vaginal pessary are common options, and some mild prolapses need no active treatment at all.
General overviews from the Cleveland Clinic and Johns Hopkins Medicine describe the condition, but UK diagnosis and care should follow the NHS, NICE and RCOG routes used here.
What is vaginal prolapse?
The pelvic floor is a group of muscles and supporting tissues beneath the bladder, womb and bowel. When that support weakens or stretches, one or more organs can move down and bulge into the vagina. The broader medical term is pelvic organ prolapse.
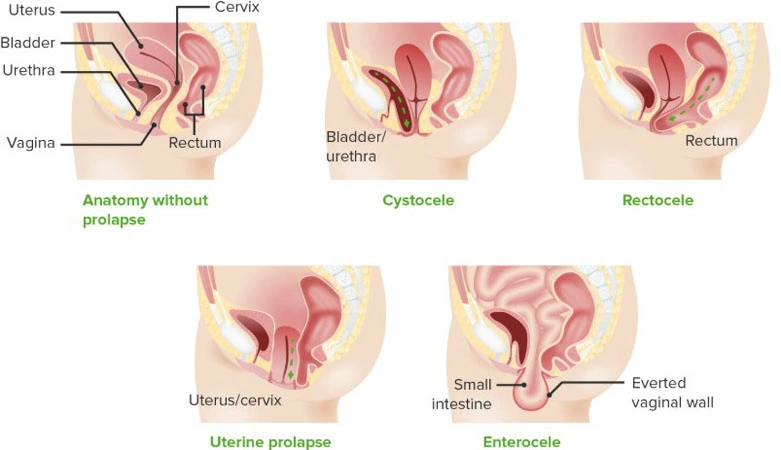
Clinicians may describe it by the part involved:
- anterior-wall prolapse or cystocele: the bladder bulges into the front vaginal wall
- posterior-wall prolapse or rectocele: the rectum bulges into the back vaginal wall
- uterine prolapse: the womb moves down into the vagina
- vault prolapse: the top of the vagina moves down after a hysterectomy
More than one type can occur together. A clinician may grade prolapse from stage 1 to 4, but symptoms and effect on daily life matter as well as the measurement. A small prolapse can feel bothersome; a larger one is not always painful.
What does prolapse feel like?
Possible symptoms include:
- heaviness, pressure, dragging or discomfort in the vagina or lower tummy
- a lump or bulge that you can feel or see in or outside the vagina
- symptoms that become more noticeable after standing and ease when lying down
- needing to pee more often, leaking, difficulty starting or a feeling the bladder has not emptied
- constipation, incomplete bowel emptying or needing to press near the vagina to help
- pain, numbness, reduced sensation or worry during sex
Those symptoms can also have other causes. Do not diagnose the type by looking at a diagram or photo. The NHS advises seeing a GP for a lump in or around the vagina or any other prolapse symptoms.
The NHS pregnancy guide covers broader antenatal care, and NHS trying to get pregnant is the NHS starting point before conception. Neither can diagnose the type or degree of a prolapse.
Can vaginal prolapse happen during pregnancy or after birth?
Pregnancy and childbirth can stretch the pelvic floor and are recognised risk factors, but symptoms may appear during pregnancy, soon after birth or years later. Ageing, menopause, being overweight, persistent constipation or coughing, heavy lifting, previous pelvic surgery and some connective-tissue conditions can also contribute. Often there is more than one factor, and it is not your fault.
If you are pregnant and notice a bulge, new bladder trouble or pelvic pressure, tell your midwife, maternity unit or GP. They can check whether it is prolapse and whether another pregnancy problem needs attention. Your individual symptoms, pregnancy stage and birth history guide care; an internet stage chart cannot decide how or where you should give birth.
After birth, heaviness and leaking deserve assessment rather than a “welcome to motherhood” shrug. The postpartum recovery guide explains other bladder, bowel, wound and pelvic-floor signs to mention. Recovery can continue beyond the six-to-eight-week check, but you do not have to wait for that appointment if something worries you.
What happens at a prolapse appointment?
The clinician will ask what you feel, when it is worse, how you pee and open your bowels, whether sex is affected and whether you plan future pregnancies. They may offer a urine test and, for bladder symptoms, a bladder scan or specialist tests.
Diagnosis usually involves an internal vaginal examination, sometimes lying on your side and sometimes standing. You may be asked to cough or bear down so the movement can be seen. You can ask for a female clinician where available, request a chaperone, bring someone you trust and ask the examiner to stop at any point. Tell them if an intimate examination is difficult because of pain, anxiety, trauma or abuse.
Useful appointment questions are: Which organ is involved? How severe is it? Which symptom is the treatment meant to improve? What happens if I wait? How do pregnancy plans change the choices?
What can help without surgery?
Watch and review
If there are no symptoms or they do not bother you, no active treatment may be needed. Symptoms can stay similar, worsen or sometimes improve. Agree what change should bring you back rather than assuming “wait and see” means never mention it again.
Pelvic-floor physiotherapy
A specialist pelvic-health physiotherapist can check whether you are squeezing and relaxing the right muscles and build a programme around your symptoms. Exercises may improve symptoms but do not guarantee that a prolapse disappears. More squeezing is not always better; pain, over-tight muscles and poor technique need individual assessment.
Reduce avoidable strain
Managing constipation, treating a persistent cough, stopping smoking, adjusting heavy lifting and finding activity that does not aggravate symptoms can help. Weight discussions should be respectful and practical. If pregnancy weight is worrying you, our pregnancy weight guide explains why dieting is not recommended; persistent cough in pregnancy also deserves proper advice rather than endless straining through it, as covered in the pregnancy cough guide.
A vaginal pessary
A pessary is a removable plastic or silicone device fitted in the vagina to support the pelvic organs. It can suit people who want to avoid or delay surgery, including some who may want future pregnancies. Finding the right shape and size can take more than one fitting. It needs an agreed removal, cleaning and review schedule; report bleeding, pain, discharge, difficulty passing urine or concern that it is stuck.
Vaginal oestrogen after menopause
For someone who has gone through menopause, a clinician may discuss vaginal oestrogen for discomfort and tissue symptoms. It is not a treatment to start independently during pregnancy.
When is surgery considered?
NICE recommends offering surgery when symptoms have not improved with non-surgical treatment or when someone has declined those options. The procedure depends on the organs involved, general health, bladder and bowel symptoms, sexual preferences and future pregnancy plans. RCOG notes that people planning more children may be advised to delay surgery because another pregnancy and birth can increase recurrence risk.
No operation guarantees a permanent cure. A proper discussion should compare doing nothing for now, continued non-surgical care and the realistic benefits, recovery, recurrence risk and possible effects on bladder, bowel and sexual function for each operation. A birth plan can record current pelvic symptoms and examination preferences, but surgical choices need a gynaecology or urogynaecology consultation.
A US legal article discusses what can be used instead of mesh for prolapse. It is not UK clinical guidance; use the treatment discussion below to prepare questions for a specialist who knows your examination and priorities.
What about vaginal mesh?
The old version of this article wrongly suggested that vaginal mesh was often inserted as a routine next step. Current NHS guidance says surgery that places supportive mesh inside the vagina for prolapse is no longer done on the NHS unless there is no alternative.
That is not the same as saying the word “mesh” never appears in prolapse surgery: some abdominal or keyhole operations use mesh in a different route. NICE says long-term effectiveness and adverse effects have uncertainty, particularly for mesh procedures, and decisions require detailed specialist discussion. If you already have mesh and have pain, bleeding, discharge, urinary or bowel trouble, painful sex or another concern, speak to your GP or surgeon.
When should you seek quicker help?
Book a GP or maternity assessment for any new vaginal lump or prolapse symptom. Ask for same-day advice from your maternity unit, GP or NHS 111 if you cannot pass urine, have severe or rapidly worsening pain, fever, heavy or unexplained bleeding, damaged-looking exposed tissue, or feel acutely unwell. Call 999 for a life-threatening emergency.
If you are pregnant, heavy bleeding, severe abdominal pain, faintness or later-pregnancy concerns such as reduced movements need the appropriate urgent maternity route rather than being blamed on prolapse. The early-pregnancy bleeding guide explains where to call, and signs of labour covers late-pregnancy changes.
Common questions
Can pelvic-floor exercises cure a prolapse?
They can improve symptoms and support the pelvic floor, especially with supervised technique, but may not remove the bulge. A specialist physiotherapist can tailor the programme and check that another problem is not being missed.
Can you have sex with a prolapse?
Many people can, but comfort varies. Some pessaries allow sex and others may be removed first after you have been shown how. Pain, bleeding, fear or changed sensation is worth discussing; you never need to continue through pain.
Does a prolapse always get worse?
No. Symptoms may stay the same, improve or worsen, and severity is not predictable from one day. Review is sensible if the bulge changes or bladder, bowel, pain or sex symptoms affect daily life.
Can you get pregnant with a prolapse?
Future pregnancy can be possible, but the type and severity of prolapse, current treatment and previous surgery matter. Ask a GP, maternity team or urogynaecologist for personal pre-pregnancy advice. The generic pregnancy hub cannot replace that plan.
Can prolapse affect mental health?
Embarrassment, pain, sex changes and loss of confidence can take a real toll. Tell the clinician about emotional as well as physical impact. Our pregnancy mental-health guide explains routine and urgent support, and the pregnancy anxiety guide may help you prepare for an intimate examination.
The bottom line
Vaginal prolapse is a bulge of one or more pelvic organs into the vagina. A lump, heaviness, bladder or bowel changes and discomfort are reasons to book an assessment without shame. Many people do not need surgery: pelvic-health physiotherapy, reducing strain and a fitted pessary can help. Surgery is a shared decision, and transvaginal mesh is not routine NHS treatment.
Sources reviewed
Editorial check: KidsCo Editorial Team, 6 August 2026. This is general UK pelvic-health information, not a diagnosis or individual pregnancy, pessary or surgery plan.


