


The earlier the scan, the more likely time—not bad news—is the reason an answer is unclear
Early Pregnancy Scan: When You Need One and What It Can Show
Quick answer: most uncomplicated pregnancies do not need a scan before the routine 11-to-14-week dating scan. An earlier scan may be offered for bleeding or pain, ectopic-pregnancy risk, fertility treatment, uncertain dates, previous complications or another clinical reason. It can check where the pregnancy is, how many pregnancies are visible and whether development matches what can reasonably be seen at that stage. A scan done very early may be inconclusive. That is a reason for planned follow-up—not, by itself, a diagnosis of miscarriage.
An early pregnancy scan is often called a viability, reassurance or dating scan, but those labels are not interchangeable. A clinical scan for one-sided pain is trying to locate the pregnancy and exclude an urgent problem. A private reassurance scan may simply offer a snapshot on a day when there are no symptoms. The question being asked determines the right route and what the result can mean.
Use the NHS pregnancy guide for the complete antenatal pathway. If pregnancy is still being planned, NHS trying to get pregnant covers folic acid, medicines and pre-pregnancy health. This guide starts after a positive test, when you are deciding whether an early scan is useful or interpreting what one has shown.
What is an early pregnancy scan?
Ultrasound uses sound waves to build pictures of structures inside the body; it does not use X-rays. The current NHS: ultrasound scans in pregnancy information says scans have no known side effects for the pregnant person or baby and can be carried out at any stage when there is a reason.
In England, the routine dating scan is offered at 11 to 14 weeks and the physical-conditions screening scan at 18 to 21 weeks. An “early” scan usually means one before that dating appointment. It is not an extra national screening test and it cannot replace either routine scan.
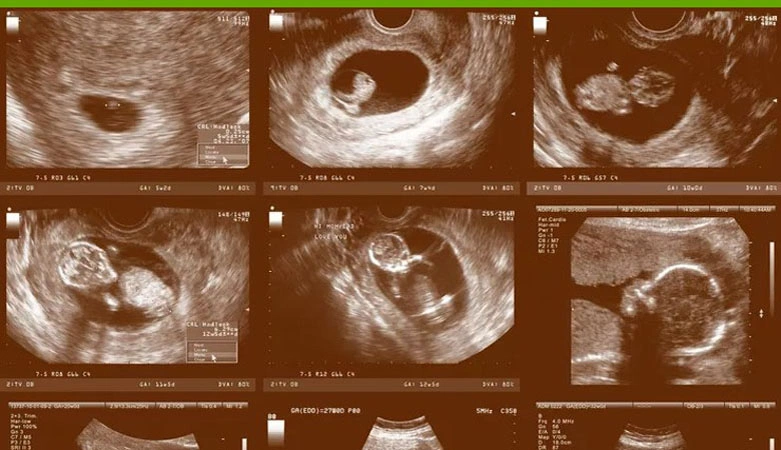
At this stage, ultrasound may be used to locate the pregnancy inside the womb, look for a gestational sac, yolk sac and embryo, check for cardiac activity when development is far enough along, estimate size and look for more than one pregnancy. The exact list depends on the clinical question, scan route and what is visible—not on the package name printed by a clinic.
A scan can answer an important question without answering every question. It cannot guarantee the rest of the pregnancy, rule out every physical or chromosomal condition, predict a later complication or prove that a new symptom is harmless. For the complete sequence of NHS appointments and what later screening is designed to assess, use the KidsCo pregnancy ultrasound timeline.
Why might an early pregnancy scan be offered?
An NHS team may recommend an early scan because the result could change care. Local referral rules differ, so not everyone with the same history is scanned on the same day. Common reasons include:
- vaginal bleeding, pelvic or abdominal pain, or another symptom that needs assessment;
- a previous ectopic pregnancy, tubal surgery or another factor that raises ectopic risk;
- pregnancy after IVF or another fertility treatment, when dates and location need checking;
- uncertain dates, irregular cycles or a discrepancy between dates, symptoms and test results;
- previous pregnancy loss or recurrent miscarriage where a local service has offered a follow-up pathway;
- a pregnancy test or hormone trend that needs to be interpreted with symptoms and imaging; or
- another individual reason identified by the GP, midwife, fertility clinic or Early Pregnancy Assessment Service.
Bleeding and pain are common and many pregnancies continue normally, but they are not symptoms to self-triage with a commercial booking. Current RCOG: bleeding and pain in early pregnancy information says to seek medical advice. Assessment may include urine testing, ultrasound, examination and blood tests. The UCLH: early-pregnancy scans for pain and bleeding page similarly explains that symptoms can have harmless causes but miscarriage and ectopic pregnancy must be considered.
The KidsCo bleeding in early pregnancy guide sets out the UK routes by symptom severity. If you already have an Early Pregnancy Assessment Service number or a plan from a fertility clinic, use that service’s instructions rather than waiting for an article, test app or private appointment.
What can a scan show at 5, 6, 7 or 8 weeks?
Pregnancy weeks are conventionally counted from the first day of the last menstrual period, not conception. That estimate assumes a cycle pattern that many people do not have. Later ovulation, an uncertain last period or recent contraception can make a pregnancy younger than the calendar suggests. NICE therefore says the last period alone must not decide whether a heartbeat should be visible.
RCOG notes that an intrauterine pregnancy may not be visible until about three weeks after conception—at least five weeks from the last period. Even then, there is no universal day on which every structure appears. This table describes the question a scan may answer, not a pass-or-fail timetable.
| Estimated timing | What may be visible | What a limited view means |
|---|---|---|
| Before 5 weeks | A urine or blood test can be positive before a pregnancy is visible on ultrasound. | An empty uterus may simply mean it is too early, but symptoms and ectopic risk still decide the follow-up route. |
| Around 5 weeks | A small gestational sac may be seen with transvaginal scanning; a yolk sac may appear as development progresses. | Seeing a sac-like structure is not always enough to establish every answer. Location, measurements and follow-up matter. |
| Around 6 weeks | A yolk sac and small embryo may become visible, and cardiac activity may be seen. | Not seeing an embryo or cardiac activity on one date does not diagnose loss. Dates, measurements and scan route determine when to repeat. |
| Around 7 to 8 weeks | The embryo and cardiac activity are often easier to identify and crown–rump length may help date the pregnancy. | Individual variation and uncertain dates still matter. A clinical team applies measurement-based criteria, not the week label alone. |
| 11 to 14 weeks | The routine NHS dating scan measures the baby, estimates the due date, checks for more than one baby and can include combined screening if chosen. | An earlier reassuring scan does not replace this appointment or its screening choices. |
The plain-language explainer Can I have a scan before 10 weeks? describes why very early timing can limit the view. For decisions in the UK, use the NHS, NICE and your own maternity or early-pregnancy service as the authority.
If your dates seem different after a scan, that does not mean you caused a problem. A due date calculated from a last period is an estimate. The routine dating scan may adjust it using measurements. The KidsCo due date calculator explains the starting estimate, while the 6 weeks pregnant and 8 weeks pregnant guides give stage context without turning a calendar into a diagnosis.
Abdominal or transvaginal scan: what is the difference?
A transabdominal scan moves a probe over gel on the lower tummy. A fuller bladder may lift the uterus and improve the view, so the appointment instructions may ask you to drink water and avoid emptying your bladder. It offers a broader view but can show less detail when the pregnancy is very small.
A transvaginal scan uses a slim, covered ultrasound probe placed gently inside the vagina. It sits closer to the uterus and usually gives a clearer early image. The probe does not enter the womb or touch the pregnancy. RCOG states that neither abdominal nor transvaginal scanning increases the risk of miscarriage.
The clinician should explain why an internal scan is recommended and ask for consent. You can ask questions, request a chaperone, say if insertion is painful, pause or stop the examination, or decline it. If you do not accept a transvaginal scan, NICE says an abdominal scan should be offered with an explanation of its limitations. Declining one route is not consent to a different procedure.
Follow the specific bladder instructions from the service because they differ by scan type. Tell the clinician about bleeding, pain, previous ectopic pregnancy, fertility treatment, pelvic surgery and the date of the last period. Bring relevant letters or hormone results if the referring team asks. Ask in advance whether a partner can attend and whether children are allowed; hospital policies vary.
What can common early-scan results mean?
The result is more than “heartbeat” or “no heartbeat”. The sonographer combines location, structures, measurements, symptoms and previous results. These are common terms and the usual logic behind them:
| Wording you may hear | What it means | Usual next step |
|---|---|---|
| Intrauterine pregnancy with expected development | The pregnancy is seen inside the womb and the visible structures match the stage assessed. | Continue the care plan and still attend routine NHS screening. Seek advice for any new concerning symptom. |
| Pregnancy of unknown location (PUL) | The test is positive but no pregnancy has yet been located on the scan. | Follow-up may include symptoms review, hCG blood tests and another scan until an early intrauterine pregnancy, miscarriage or ectopic pregnancy is identified. |
| Intrauterine pregnancy of uncertain viability | A pregnancy is visible in the womb, but the measurements and structures do not yet prove whether it is developing. | A repeat scan after the minimum safe interval gives time for a real change that can be interpreted accurately. |
| Threatened miscarriage | There has been bleeding or pain, but the scan shows an intrauterine pregnancy progressing at that assessment. | Follow the unit’s advice and return for worsening symptoms; a follow-up scan may be offered. |
| Suspected ectopic pregnancy | The findings, symptoms or hormone pattern suggest a pregnancy may be developing outside the womb. | Urgent specialist follow-up is required. Management depends on the complete clinical picture, not a home test or one number. |
| Miscarriage diagnosed | The clinical team has applied ultrasound criteria, sometimes with a second opinion or repeat scan, and concluded the pregnancy is not continuing. | The team should explain expectant, medical and surgical options where applicable, what to expect and how to get support. |
The historic NHS notes explain that ultrasound has different purposes at different stages. The broader NHS- Ultrasound scans in pregnancy explainer also makes the essential limitation clear: even a normal-looking scan cannot identify every condition.
An early scan can sometimes show more than one gestational sac or embryo. The maternity team may need a later scan to confirm how twins share placentas and sacs, which affects monitoring. It is also too early to use genital appearance to assess sex. The KidsCo guide to the limits of sex clues on ultrasound covers the later scan context.
What happens if the scan result is uncertain?
Uncertainty is a defined clinical state, not a euphemism for a diagnosis that staff are withholding. There may not yet have been enough development to interpret safely, the dates may be off, or the pregnancy may not yet have been located. The next step exists to separate those possibilities.
Current NICE early-pregnancy ultrasound guidance, updated in June 2026, says one scan cannot guarantee a miscarriage diagnosis is 100% accurate, especially at very early gestations. Clinicians first look for cardiac activity and then apply crown–rump length or gestational-sac measurements. Those measurements—not a week-counting app—set the safe decision rules.
When a transvaginal view is below or reaches specified thresholds without the expected structure, NICE requires a second opinion and/or a repeat scan at least seven days later before diagnosis. Corresponding uncertain abdominal-scan findings require at least 14 days. Further scans can be needed. These intervals should not be shortened just to end the wait sooner: NICE states that waiting for the repeat scan does not harm the pregnancy outcome.
With a PUL, blood tests may measure hCG twice, as close as possible to 48 hours apart, and a repeat transvaginal scan may follow. A rising number does not by itself prove the location or exclude ectopic pregnancy. Symptoms take priority over a previous result or hormone trend, and follow-up continues until the location or outcome is established.
If tests become negative before a pregnancy was visible, the KidsCo chemical pregnancy guide explains the terminology and follow-up. If the waiting period is consuming sleep or daily life, the pregnancy anxiety guide gives practical UK support routes. Neither page replaces the safety instructions from the early-pregnancy team.
When do bleeding or pain need urgent help?
Do not wait for a routine or private scan if symptoms need assessment. Contact your GP, midwife, NHS 111 or Early Pregnancy Assessment Service for bleeding or pain in early pregnancy, following any direct local plan you have already been given.
Get immediate assessment for heavy bleeding, severe abdominal or pelvic pain, shoulder-tip pain, marked dizziness or fainting. Go to A&E or use the urgent route your Early Pregnancy Assessment Service gave you. Call 999 for sudden intense pain with collapse, fainting, severe dizziness or another life-threatening emergency.
The current NHS ectopic-pregnancy symptoms page also lists one-sided lower tummy pain, unusual vaginal bleeding and discomfort using the toilet. Some people have no symptoms initially, so a PUL follow-up plan must be completed even if they feel well.
A scan that previously appeared reassuring does not cancel new symptoms. Nor should a private clinic simply tell you to book another paid scan if its findings or your symptoms need NHS assessment. Ask exactly which service to contact, how quickly and what information will be transferred.
Should I book a private reassurance scan?
A private scan can be a reasonable personal choice when you understand its limits. It may provide useful information at that moment, but it can also create more uncertainty if booked too early. Media reports have called the cycle of anxiety and repeated reassurance “scanxiety”. More scans are not automatically more reassuring if nobody has agreed what question is being answered or what happens after an unclear result.
In England, start with CQC: choosing a baby scanning service. Diagnostic and souvenir ultrasound providers should be registered with the CQC. Registration is a baseline check, not a promise that every package or operator is right for your situation.
Before paying, ask:
- What am I buying? Is this a diagnostic early-pregnancy scan, a non-diagnostic souvenir service or a combination?
- Who performs it? What ultrasound training, professional registration and early-pregnancy experience do they have?
- Is the timing sensible? What can the clinic reasonably expect to see at your estimated gestation, and will it explain the risk of an inconclusive scan?
- Which route is included? Is the appointment abdominal only, or can a clinically appropriate transvaginal scan be offered with consent and a chaperone?
- What report will you receive? Ask whether it records location, measurements, visible structures, limitations and the operator’s name.
- What happens if there is concern? The clinic should have a clear escalation and referral route, not leave you to interpret an image or arrange serial paid scans.
- How is your information handled? Ask how reports and images are stored, shared with NHS care and deleted.
- What is excluded? A reassurance scan does not replace routine dating, screening, anomaly or symptom-led NHS care.
Price, a luxury room, video clips and a heartbeat recording do not establish clinical quality. The CQC advises asking about the operator’s qualifications and whether they appear on an appropriate register. “Sonographer” itself is not proof of a particular professional registration, so ask for the specific qualification rather than relying on a title.
How should I prepare and what should I ask?
Read the appointment instructions before drinking water or emptying your bladder. Write down the first day of the last period, usual cycle length, pregnancy-test dates, fertility treatment dates and relevant previous pregnancies or surgery. Bring a medication list and any referral letter, hormone results or earlier scan report requested by the service.
During the appointment, the operator may need quiet time to examine the images before talking. Ultrasound is a medical examination and can occasionally find unexpected news. You can ask whether results will be explained immediately, whether a written report is provided and whether a support person can be present.
Useful questions after the scan are:
- Was the pregnancy located inside the womb?
- Which structures and measurements were seen, and which were not yet expected?
- Does the result answer today’s clinical question, or is it classed as uncertain?
- Do I need blood tests, a repeat scan or routine antenatal care only?
- Exactly when should follow-up happen, and who is responsible for arranging it?
- Which symptoms should change the plan, and what 24-hour number should I use?
Do not compare a still image, measurement or heart-rate number with an online chart and diagnose the pregnancy yourself. The scan route, image quality, exact measurement technique, symptoms and sequence over time all matter. Ask the clinician to translate the result into a clear next action.
Common questions about early pregnancy scans
What is the earliest week an ultrasound can show a pregnancy?
A pregnancy may begin to be visible with transvaginal ultrasound from about five weeks after the last period, but that is not a guaranteed appointment date. Before or around five weeks, a positive test with no visible pregnancy can simply be too early. Symptoms and ectopic risk determine how it should be followed.
Should a heartbeat always be visible at 6 weeks?
No. Cardiac activity may be seen around six weeks, especially with a transvaginal scan, but ovulation timing, cycle length, scan route and tiny measurement differences all matter. NICE says not to use the last period alone to decide whether it should be visible or to diagnose miscarriage.
Can a transvaginal scan cause miscarriage?
RCOG states that neither a transvaginal nor an abdominal ultrasound increases miscarriage risk. The internal probe sits in the vagina, not inside the womb. The examination still requires explanation and consent, and you can ask for a chaperone or stop at any time.
Do I need a full bladder for an early pregnancy scan?
Often for an abdominal scan, yes; usually for a transvaginal scan, no. Instructions vary by service and the planned examination. Follow the clinic’s directions rather than drinking excessive water automatically, and ask if the route changes during the appointment.
What does an empty scan mean after a positive test?
It can mean the pregnancy is too early to see, an early loss has occurred or the pregnancy is ectopic and not yet visible. Until the location or outcome is established, this may be called a pregnancy of unknown location. Complete the blood-test and repeat-scan plan and seek urgent help for worsening symptoms.
Why do my scan dates differ from my last period?
Last-period dating assumes a cycle and ovulation pattern that may not match yours. Later ovulation can make an early pregnancy appear younger. A very small early measurement also has limited precision. The routine dating scan uses later measurements to estimate the due date more reliably.
Can an early scan show twins?
It may show more than one gestational sac or embryo, but a very early view can be incomplete. A later scan may be needed to confirm the number of babies and how placentas and sacs are shared. Keep the routine dating appointment even if twins appear on a private scan.
Does a private reassurance scan replace the NHS dating scan?
No. A private early scan is a snapshot and does not replace the NHS 11-to-14-week dating and screening appointment or the 18-to-21-week physical-conditions scan. It also must not delay NHS assessment for bleeding, pain or ectopic-pregnancy symptoms.
The bottom line
An early pregnancy scan can be clinically important when it answers a defined question about location, symptoms, dates or development. Its usefulness depends on timing and scan route. The earlier it happens, the more often the honest result is “not enough information yet”.
Do not let a week-counting app turn an uncertain scan into a diagnosis. Follow the measurement-based repeat plan, complete PUL monitoring and make sure you have a 24-hour symptom route. For a private scan, check CQC registration, operator qualifications, report scope and escalation before paying—and still attend routine NHS screening.
Sources reviewed
Editorial check: KidsCo Editorial Team, 10 August 2026. This is general UK pregnancy information, not a diagnosis or individual care plan.
- NHS guidance on ultrasound scans in pregnancy and ectopic-pregnancy symptoms
- NICE guideline NG126, updated June 2026, on pregnancy location, viability and repeat scans
- RCOG patient information on bleeding and pain in early pregnancy, reviewed August 2025
- Care Quality Commission guidance on choosing a private baby scanning service
- University College London Hospitals information on early-pregnancy pain, bleeding and assessment
Continue with useful pregnancy guidance
- See the complete NHS pregnancy scan timeline
- Know what to do about bleeding in early pregnancy
- Understand a chemical pregnancy and follow-up
- Estimate your due date before the dating scan
- Read the 6 weeks pregnant guide
- Read the 8 weeks pregnant guide
- Prepare for 12 weeks and the dating scan
- Find support for pregnancy anxiety


